Caption from the Medscape Instagram post in the photo, which I re-shared on my stories:
“Patients who use gray-market retatrutide seemed to achieve roughly half the expected weight-loss benefit relative to Eli Lilly’s clinical trials of the drug, while still experiencing high rates of cardiovascular effects, researchers reported in a preprint study.
“At this time, retatrutide isn’t approved by the FDA and is in phase 3 clinical trials. The company has announced plans to submit for drug approval in first quarter 2027. However, demand for the triple-agonist has surged. Read more about the research by tapping the link in our bio.” Read the Medscape article itself.
Ooo, lots to discuss here friends! Let’s see if I can be thoughtful, informative and concise! I’ll give a brief summary of the Instagram post referenced above, implications I see as a physician, and my conversation with Friend who actually tried retatrutide from the gray market.
Retatrutide represents the next generation of medication for metabolic conditions like diabetes and obesity, and it shows tremendous effectiveness for the latter. In a phase 2 trial published in 2023, the vast majority of study participants lost at 10-15% of their body weight on the highest doses. Interestingly, about a quarter of patients taking placebo also lost 10%, and also experienced a noticeable amount of side effects–but that’s for another post. One phase 3 trial showed just under 2% decrease in hemoblobin A1c (the three month average blood glucose test, which we follow in patients with diabetes, and 2% change is significant) and 15% decrease in body weight at the highest dose.
The study (yet unpublished) referenced in Medscape is fascinating: nference, an AI company that works with clinical entities to convert medical records to de-identified data, mined clinical notes for signs that patients were using retatrutide, even though it’s not FDA approved and cannot be formally prescribed (and thus not yet monitored or tracked in any accountable way). Some exerpts:
“Unlike most retrospective observational studies, which start from a prescription or pharmacy claim, the researchers used large language models and de-identified electronic health records (EHRs) from US academic medical centers and health systems to capture the complete clinical note history of patients taking retatrutide.
“’Retatrutide isn’t an approved product, so it has no national drug code, no pharmacy claim, and no structured prescription record anywhere in the health system,’ Soundararajan explained. ‘Evidence about who is taking it exists only in the physician narrative in the form of free text in clinical notes.’
“Using the nference AI platform, the researchers retrieved the full clinical-note history for every patient whose record mentioned the drug and adjudicated three outcomes: whether the patient actually took the drug; where they obtained the drug; and when they started taking the drug. A clinician manually re-reviewed 320 randomly sampled extractions against the source notes. Exposure classification was 99.8% accurate and supply route was roughly 90% accurate.
“Analyses showed a rapidly increasing use of nontrial products purported to contain retatrutide, with a 1.8-fold increase per quarter from October 2023 through March 2026.
“Weight loss among the 89 retatrutide trial participants was 15.5% at 6-12 months, closely approaching the observed 16.9% mean weight loss across the retatrutide and placebo arms at 80 weeks after treatment initiation in TRIUMPH-1-4 (weighted average).
“In contrast, compounded retatrutide users lost 7.2% body weight at 6-12 months, less than the 15.5% observed in the retatrutide trial cohort and comparable to the weight-loss achieved among matched tirzepatide users (7.7%).
“A significant increase in heart rate was observed at 3 months for both the retatrutide trial cohort (+4.3 beats per minute [bpm]) and the compounded retatrutide cohort (+2.5 bpm), which was not seen in the matched semaglutide or tirzepatide cohorts.
“The retatrutide trial cohort also showed numerically higher, but not statistically significant, rates of three-point major adverse coronary events (MACEs) vs matched tirzepatide users (relative risk [RR], 1.77) and semaglutide users (RR, 1.02), with similar findings for expanded MACE vs tirzepatide (RR, 2.03) and semaglutide (RR, 1.25).
“Limitations included the observational nature of the study, which precludes proof of cause; short and uneven follow-up (median roughly 3 months in the retatrutide arms vs 6 months in comparators); and index dates derived from notes rather than dispensing records.”
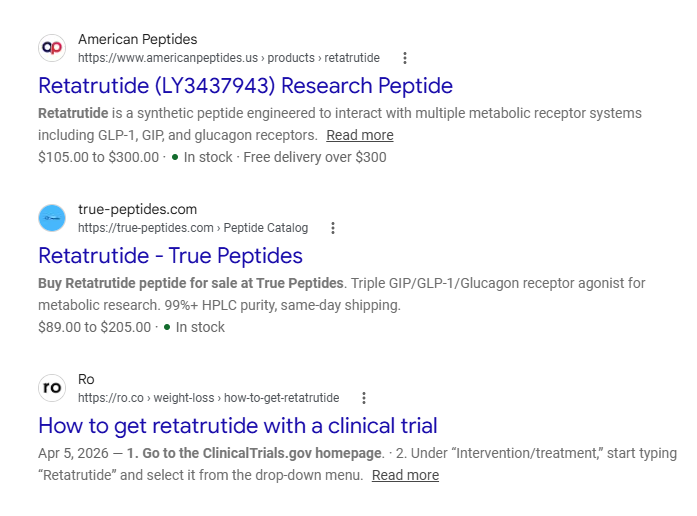
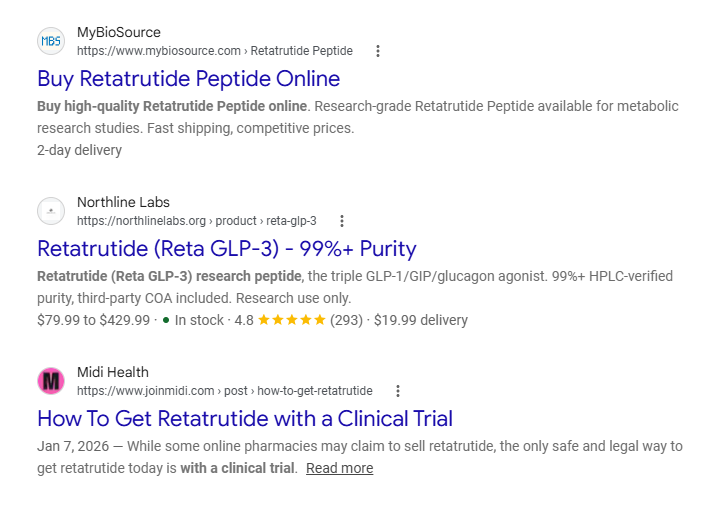
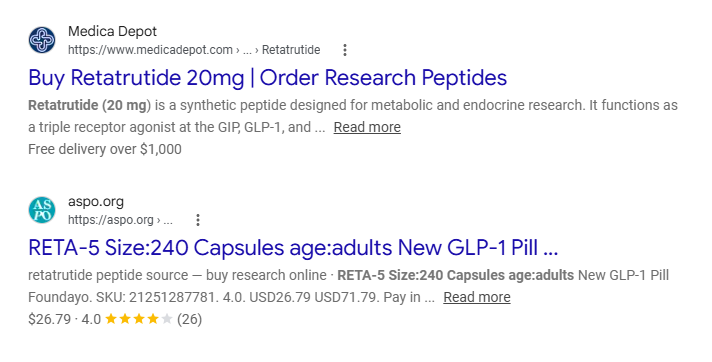
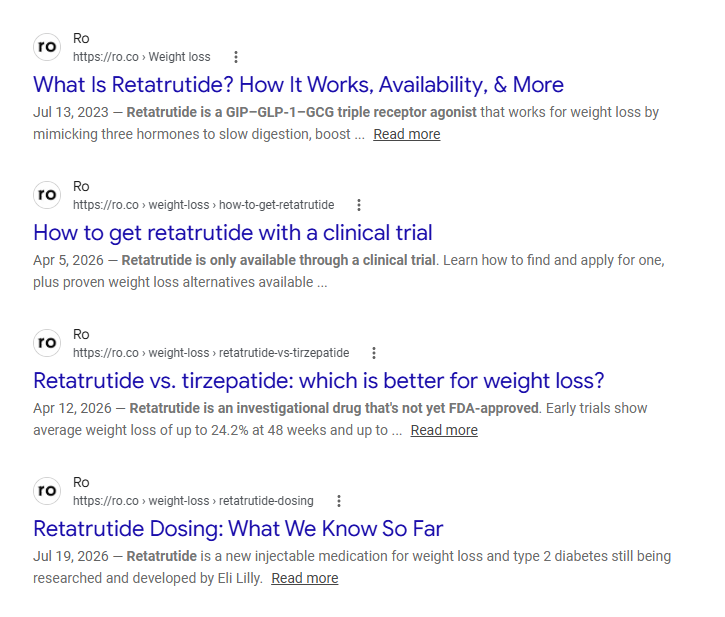
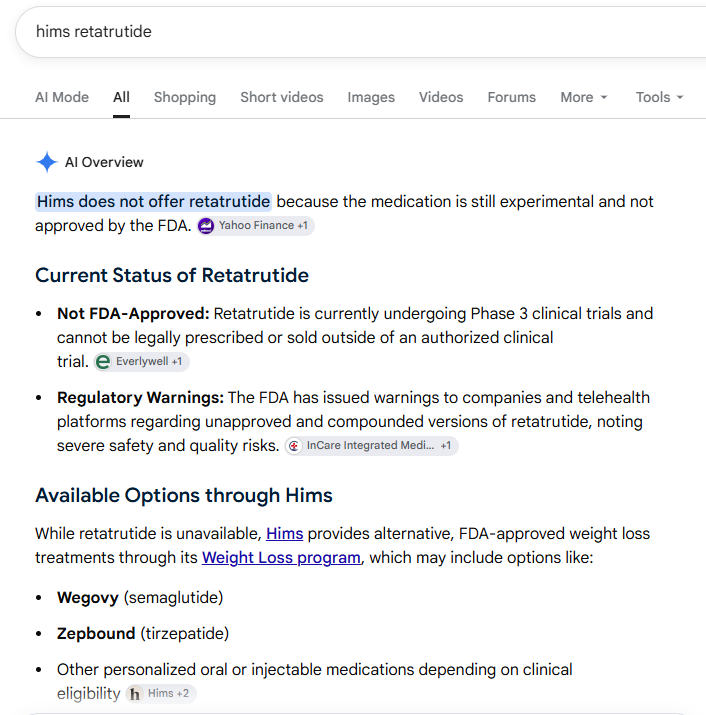
See below for screen snips of results from my Google search, “get retatrutide online.” Online pharmacies like HIMS and Ro, which provide compounded versions of FDA approved weight loss drugs, do not provide retatrutide. Most of the hits were peptide sellers, though platforms like Ro and Midi look like they give information on how to seek the medication through research trials.
I spend an increasing proportion of my practice discussing and dispelling medical misinformation. It eats all kinds of time, but I welcome it because I learn so much, and my practice is sturctured such that I have the time, which most doctors do not. I learn what my patients are seeing, hearing, and thinking. We look up evidence together, and I get to explain how I vet information: sources, physiology, rationale, conflicts of interest, meaningful outcomes, and the balance of benefit, cost, and risk. We learn together and I earn trust. My perspective shifts and I gain flexibility while hewing close to strong medical ethics and high academic and public health standards. I was both interested in and validated by Dr. Karl Nadolsky’s Instagram story, so I shared it.
My gym friend commented, “Let’s chat about this,” and now blog readers and I all get to benefit from the follow up. Friend has agreed for me to share our conversation with a few key quotes here.
Friend: “I tried grey market Reta and had zero results. zero. 16 weeks, titrated up doses. Actually gained weight and body fat. Mentioned it in a few body building and CrossFit forums and others had similar results with the Chinese labs products like Reta.
Turns out, from those who sent the products out for lab testing, that there’s enough of the product in the vials to show that the actual chemical formula is present, but it’s severely underdosed to what they’re selling… The TRT [testosterone replacement therapy] clinics are selling Reta for over $300 for a 3ml vial of 15mg/ml. That’s down from $750 a few months ago. The Chinese grey market sells them for $35-$50 per vial. So gym bros, who are already spending on memberships, protein, supplements, and testosterone see the cheap prices and jump on them… One of the more popular online forums for gym bros is called “steroid source talk”, and there is where thousands of contributors share results and product reviews. There’s even links to vendors that have proven to have decent quality product.”
Let’s take a moment here. What do we notice in ourselves when we read this? What assumptions do we make, and what do we judge, especially?
Whenever I talk with a patient or friend about these things, especially someone with first hand experience, my attitude softens significantly. It’s not unlike my conversations with Red voting friends. I have my biases and convictions about public health, evidence-based medicine, affordable healthcare, etc., and they have theirs. I also care a lot about connection and relationship, which only occurs with openness, curiosity, and humility on both sides.
I messaged my friend, “It’s all so fascinating. I’m so interested in the motivation, the drive to seek these things. What’s at the heart and bottom of it, what need does it meet? Our culture is evolving so fast and so much of it feels mindless and numbing to me, like the worst of human nature is behind the wheel (collectively) too often.”
He answered, “Follow the marketing, in my opinion. It targets a specific demographic. Middle aged men, who work out tirelessly, are fathers, business owners, husbands, and are simply frustrated and aggravated with their current progress or results. They’re lifting weights constantly and not getting stronger. They’re dieting daily, tracking macros, eating whole organic foods, but are still appearing soft, and aren’t shedding stubborn fat that would come off easily in their 20s or 30s. The marketing is targeting a specific population demographic that has a ‘problem’, …self-perceived or not, and offering a ‘solution.’ …These men… are essentially desperate to see better progress, and (the companies) prey on that vulnerability. One of the most successful clinics in Chicago uses the phrase ‘get your mojo back’ on all their ads.”
Me: “…I’m thinking it’s similar for women…cultural expectations and pressures to stay young, beautiful, etc. *sigh*” [And now that I re-read, this intersects with last week’s post about pathologizing the normal, making women expect that they should not have to feel or experience the changes of menopause, that it can somehow be eradicated…] “I think our culture really fears aging and losing function. This intersects with how we don’t value our elderly, as if they have nothing to contribute. It’s all very complex and ties into our individualist, money-driven culture traits, too—very American, or at least Western. I often find myself comparing and contrasting this mindset with how I experience Chinese and Eastern culture, which is very much more respectful of elders and, in my observation, a lot less fearful of aging.”
In the end, my friends, what is truly worth our time, money, and energy? What do we want and what are we willing to spend, sacrifice, and risk to get it? At the end of life, what will really have mattered, and what will we look back on and wish we had let go or held onto better? What fears does the culture amplify for others’ (financial) benefit? How can we each and collectively resist such nefarious actors, and be ourselves agents of integrity, connection, wellness, self-efficacy, and grace?
I never expected that sharing an Instagram story would provoke such a dive into emerging pharmaceuticals and their ‘gray market’. But I’m not at all surprised that it opened a respectful and connecting conversation with a new friend. It reinforces to me the possibility and potential for connection in any forum, on any platform, if we are willing to engage humbly as fellow humans. Let’s spend our precious time, energy, and resources more intentionally on one another, yes?