Culture of Medicine, Part I

12657_4331869529492_1472680046_n

NaBloPoMo 2018:  What I’m Learning

Recently I met with a group of medical trainees from different institutions, ranging from pre-med to senior resident.  The topic was leadership in medicine and culture.  My objective was to lead a discussion on how we see leadership, and to encourage physicians at all levels of training to see themselves as leaders, regardless of designated status.  I often invoke Benjamin Zander’s invitation to ‘lead from any chair.’

We started out discussing the current state of medical culture.  My summary of the labels, in the order we discussed them, follows here.  I strive to hold these observations with minimal judgment, and to practice radical acceptance.  This is simply the way things are, not good or bad, it just is.  That includes how we feel about it all, and that we want to change the parts we don’t like.  Tomorrow I will continue with Part II, characteristics of Culture of Wellness leaders.  For now I invite you, especially my friends in medicine and healthcare, to review the list dispassionately, objectively, from a distance.  See how it lands.  How do you feel reading this list?

  1. Intense
  2. High stakes—we hold people’s lives in our hands.
  3. Imbalanced. When asked to say more, this trainees explained, “It encourages a lack of balance—we are not supposed to mind the long hours.  Our priorities are skewed—we say patients first (but it feels like patients above all else, at any cost?).  There’s the paperwork, the burnout.  You can’t go home if the patient needs you (internal medicine), and in some fields there is no such thing as a shift.  It never ends. (surgery)”  These trainees felt no work-life balance.
  4. Resistant to change. It’s an attitude—“When I was your age…”  Anything different and new in terms of work hours, work load, etc. is deemed bad or inferior before it’s even considered.
  5. Hostile. Between staff members, between doctors and nurses, between doctors themselves, nurses themselves.  The trainees saw this as a key contributor to everybody’s burnout.
  6. Hierarchical—especially surgery (they pointed this out explicitly). For example, walking in the halls, there is an order in which people enter patient or operating rooms.  One student reported entering before her team, because she knew the patient, and making small talk.  Later, she reported, “the senior resident yelled at me, said to go in order, and do not talk to the patient.  In 2017.”  In the OR, when students cut sutures, they must always cut the attending’s suture first.  One medical student was admonished loudly in the OR for this.
  7. “You’re expected to know everything already, even though you’re supposed to be learning on the job.” Trainees agreed that they expect to have to prepare for each day at work.  But as trainees, they cannot always know how to prioritize information as they study in advance for what feels like daily examination.  And they are belittled and shamed for not reading their instructors’ minds and knowing exactly what the teacher is asking for (‘pimping’ the students, as it’s known).  “I never feel like enough.”

At this point you may suspect that I somehow planted the seeds of negativity in these trainees’ minds, goaded them on to blast our profession and everybody who had ever said something mean to them in the hospital.  I assure you I did not, and I marveled myself at how easily these labels flew onto the table.  I hurried to take notes.

Thankfully the vibe circled, as it often does.  One woman commented:

  1. “Family medicine seems actually anti-hierarchy.” Attendings, she observed, often defer to students, who usually know the patients the best, when discussing patient history and data.  Team members may all address one another by first names.  Another student piped in:
  2. Pediatrics is similar. Attendings cover for the team during signout, answering pages and signing orders—everybody pitches in.    On rounds students are allowed to be students—to make mistakes, to show gaps in knowledge.  And a resident pointed out:
  3. In anesthesia, team members take breaks, and she felt a sense of autonomy and support of residents—no shaming. “Maybe it’s the nature of the work,” she said, “it’s easier to tag team.”

Fascinating.  I was practically trembling with excitement—here were ten strangers, from different specialties and at various levels of training, men, women, people of diverse colors and cultures.  And we all had the same experience of our chosen profession, much of it negative.  Yet here we all were, committed and still excited to be doing this work—we all still hear the call.  Whatever keeps us going?  How do we get up every morning and come to work in this ‘toxic’ environment?

I’ll tell you tomorrow.

Less Phone, More BOOKS!

books 11-3-2018

NaBloPoMo 2018: What I’m Learning

Hi, I’m Cathy, and I’m addicted to my phone.

Last month I finally decided to do something about it, mostly so I could be more present to the kids.  It’s been a fascinating journey so far, and I’m proud to say I’ve already made progress.  First I banned Facebook after 6pm.  That went well until I traveled.  Then I took the Facebook app off of my phone.  The withdrawl continues to spike at times.  I also notice that I use other things to substitute—New York Times, email, Washington Post, email, WordPress Reader, email.  I notice an anxiety, a frustration, a kind of crazed, darting hankering– I crave that dopamine hit.

The awareness of it all, however, and the commitment to get disentangled from my screen, has cleared space for a recently dormant impulse to surface afresh:

READ!

* * *

At the conference last month I was turned on to the idea of complexity (or chaos) theory and how it relates to fixing physician burnout and turning our whole medical system around.  It was positively mind-blowing (for me—most others did not seem quite as lit).  The speaker was Anthony Suchman, my newest hero.  Some highlight ideas:

  • Every system is perfectly designed to get exactly the results it gets. Our current healthcare system evolved to this point precisely from serial and cumulative decisions made over years, even though the current state was never the intent.
  • We think of organizations as machines, with predictable, linear consequences of adjustments in one part or another. This is rarely how organizations (of people) actually work.  Rather, we can think of organizations as conversations, and let go our expectations of particular outcomes, the illusion of total control.  We can let things unfold and go where the outcomes lead us, all while holding to core values and goals.
  • Patterns are (re)created in each moment, and also self-organizing. So at the same time that a pattern (eg culture) seems inevitable and self-propagating, sometimes small, almost imperceptible perturbations can create new and dramatic cascades that lead to transformation (the butterfly effect).
  • Emergent Design thus embraces the approach of “finding answers we are willing to not know,” trusting that we will get where we need to go simply because we are paying attention (or that’s how I interpret it today).

This theory that everything within a system both results from and also contributes to the whole system (a fractal) validates an idea I have been advocating to my patients for years, and that I continue to personally relearn ad nauseam: It’s all connected.  The most concrete examples are Sleep, Exercise, Nutrition, Stress Management, and Relationships—I used to call them the 5 Realms of Health; now I call them the 5 Reciprocal Domains.  Each one is inextricably connected to every other one, and they all move in concert, with subtle or dramatic dynamics.

books 11-2-18

I browsed around my local bookstore a couple weeks ago and came across a colorful title on the shelf: Emergent Strategy by Adrienne Maree Brown.  So of course I snatched it up.  The blurb says:

Inspired by Octavia Butler’s explorations of our human relationship to change, Emergent Strategy is radical self-help, society-help, and planet-help designed to shape the futures we want to live.  Change is constant.  The world is in a continual state of flux.  It is a stream of ever-mutating, emergent patterns.  Rather than steel ourselves against such change, this book invites us to feel, map, assess, and learn from the swirling patterns around us in order to better understand and influence them as they happen.  This is a resolutely materialist “spirituality” based equally on science and science fiction, a visionary incantation to transform that which ultimately transforms us.

Holy cow, YAAAAS!!  I could not wait to read it!  So I bought it, along with Make Trouble by Cecile Richards, What If This Were Enough? By Heather Havrilesky, and The Dharma of “The Princess Bride” by Ethan Nichtern.  I had also ordered Leading Change in Healthcare, coauthored by Dr. Suchman and two others.  That copy arrived last week.

Suchman 1

I feel this as all part of a slow turn, getting off my phone and diving into books again.  I’m so excited.  I have done this before—buy a bunch of books and never read them.  They occupy whole shelves in my bedroom.  But I honestly feel a transformation coming on.  Yesterday I spent a couple hours reading, researching, and writing the blog post, then I turned off the computer and opened Brown’s book.  I read through the long introduction and resonated with sentences like, “Emergence is the way complex systems and patterns arise out of a multiplicity of relatively simple interactions.”  This is a quote from Complex Adaptive Leadership: Embracing Paradox and Uncertainty by Nick Obolensky (which I have also now ordered).  I also love (ha!), “Perhaps humans’ core function is love.  Love leads us to observe in a much deeper way than any other emotion.”  Also:

all that you touch

you change

all that you change

changes you

the only lasting truth

is change

god is change

That is a quote from Parable of the Sower by Octavia Butler.

Then before bed I opened Suchman et al’s book and found these words, also in the introduction:

Complexity theory here is enriched by the focus on relationships [Hallelujah!], rather than the more traditional reference to science.  “Relationship-Centered Care” is a way of thinking that brings love and all that is personal into a world, the world of healthcare, that is mostly interested in more control and more data-based, evidence-based practices.

The point is made throughout that administrators cannot bring real change into their healthcare institutions without going through change themselves.

(The book describes) the relationship-centered social dynamics that are at the heart of Lean and a major source of this method’s success.  Unfortunately, these social dynamics are overshadowed or even displaced by the analytic technique in some Lean implementations, compromising results.

Suchman 2

So I’m learning about new ways to think on change.   It’s changing how I approach trying to change my patterns, how I see my relationship to them, how I see all relationships.  Wow.

All of this to say, I feel a deeply personal, yet global and cosmic impulse for growth, for transformation—a shift into more mindful and intentional use of my time and energy, and how I manifest it outward.  Less distraction, more focus.  Less incidental information consumption, more integrated learning and coordinated application.  Less phone, more BOOKS.

What will be the outcome?  I have no idea, that’s what makes it so exciting and wonderful!  Onward!


How Not to Engage

DSC_0353

NaBloPoMo 2018: What I’m Learning

My friend Alex* posted about being a nurse and how she loves it despite having to always hold her pee, skip lunch, and get bled on, puked on, peed on, and yelled at, all while missing her family and taking care of yours.  One of her friends, we will call him Greg, commented that until nurses unionize and demand professional respect ‘just like physicians,’ nothing will change.

My impulsive (GRRR!) response:  “Trust me, physicians are struggling, too. I propose that we stand up for one another. Then we’d really be a strong force. And in the end it benefits us all–doctors, nurses, patients, the whole care team and, most importantly, patients. Also, I don’t know of any unions that physicians can join, but there are ones that nurses can: https://nurse.org/articles/pros-and-cons-nursing-unions/”  Okay, I know, saying, “Trust me,” is not a good way to get someone to trust or listen to you.  And my reply was defensive in its origin.  I sincerely believe what I wrote, though, that allied advocacy is an untapped force for good in medicine.  Physicians, patients, nurses, all healthcare professionals—why should we not actively support one another in all of our efforts to achieve a more cohesive, efficient, fair, and collaborative system, one that works better for all of us?  Why can we not embrace our connections and combine our voices to call for change?

Greg replied that basically he does not believe that physicians are “struggling,” and he does not see how we would stand up for one another.  After Alex described that I’m a physician “who will always help the nurses,” he wrote that doctors “can’t be in the business of supporting nurses.”  That we should “be in the business of supporting” ourselves, and “from all the research I’ve ever seen, they’ve continued to do a pretty good job of it.  Good for them.”  He expressed support for physicians’ right to advocate for ourselves.  In each reply, he continued to make his point that nurses should unionize.

I find this thread fascinating.  There are so many ways Greg and I could interpret each other’s replies.  When he talks about demanding respect ‘like physicians’ through unions, what benefits and outcomes does he imagine will follow?  When I say “struggling,” I wonder what he thinks I mean?  Actually he asks me, “How exactly are physicians struggling?”  He goes on to write, “Nurses are nurses and should be for nurses.”  All of his comments and the tone I inferred from them caused me to beg off of the thread.  Too bad, it might have been an interesting conversation—if we could have it in person.  Maybe we can later.

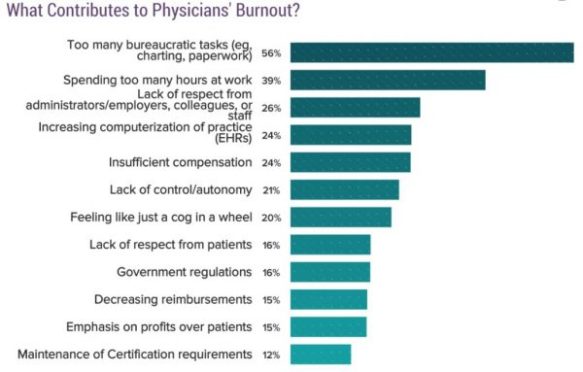
But it motivated me to look up some information to post here, in case anybody wonders ‘how physicians are struggling.’  The answer is burnout, depression, suicide, and leaving work that we love because it simply costs us too much—and I mean costs other than money.

Physician burnout is well described and referenced.

Doctors suffer from burnout in especially high numbers, according to the study, which was designed to offer a representative snapshot of doctors and the general U.S. working population. Nearly half of U.S. physicians – 49 percent – meet the definition for overall burnout, compared with 28 percent of other U.S. workers. More than 54 percent of doctors have at least one symptom of burnout, a more detailed analysis found.

Doctors also register more than one and a half times the general working public’s rates of emotional exhaustion and depersonalization. Working a median 50 hours per week, their satisfaction with work-life balance is far lower than that of others: 36 percent versus 61 percent.

medscape burnout causes 2018

Medscape Survey 2018

There are myriad causes for physician burnout, and most of them lie in the system, not in our inherent lack of resilience or because of some intrinsic defect in our collective character.  The electronic health record has accelerated our dissatisfaction with work.  It does so by creating innumerable clicks to accomplish menial tasks, burdening us with data entry that detracts from actual medical decision making and patient care, and putting a physical barrier between us and our patients, further separating us in relationship.  Burned out and dissatisfied doctors are distracted, less empathetic, and aloof, and we may even make more mistakes.  And when we aren’t well, our patients aren’t well.

A 2015 Mayo Clinic study reported that roughly 40 percent of physicians suffer depression each year and almost 7 percent had considered suicide within the prior 12 months. It is estimated that 300 to 400 doctors take their lives every year.

The pain and suffering those statistics only hint at is bad enough. But they are compounded by findings that burnout corrodes the doctor-patient relationship, resulting in lower levels of patient satisfaction, job satisfaction and productivity, as well as higher levels of medical errors and disruptive behavior.

Burnout is also connected to the decision to switch jobs or leave medicine altogether — an ominous trend as the U.S. experiences a growing doctor shortage.


I have not addressed here the challenges that nurses face every day.  My mom is a nurse, and I have worked with nurses my whole career.  I see how they are treated by the system and by patients, and also by us physicians.  And yes, my extracurricular activities focus solely on advocating for physician health and well-being.  Maybe I should learn more about nurse burnout and job satisfaction, and figure out ways to advocate for my nursing friends and colleagues better.

Or maybe it’s too much to ask for groups to stick up for one another.  Maybe Greg is right, and it should be every tribe for itself, let others take care of their own.  Maybe it doesn’t do any good for people to know how and how much doctors “struggle.”  I don’t know.  But I have learned now not to instigate such debates on my friends’ pages on social media.

*Not her real name